

Clinical trials are generating more data from more sources, while study teams are coordinating increasingly specialized workflows. Choosing clinical trial software is therefore no longer simply a question of selecting an Electronic Data Capture (EDC) system. It is about building a technology environment that can support the study from data capture through operational oversight.
The scale helps explain why this matters. A Tufts Center for the Study of Drug Development analysis of 220 completed biopharmaceutical protocols found that the average Phase III trial generated approximately 3.6 million data points, about three times the volume reported a decade earlier. The same analysis found an average of 263 procedures per participant across Phase II and III protocols supporting approximately 20 endpoints, while the mean number of distinct procedures had risen 44% since 2009. [1]
As clinical research becomes more data-rich, the software stack connecting those activities becomes part of the study’s operational foundation.
Clinical trial software now reaches far beyond the eCRF
EDC remains at the center of many clinical studies, but the information surrounding it has expanded considerably.
Clinical data may now originate from electronic Clinical Outcome Assessments (eCOA), electronic Patient-Reported Outcomes (ePRO), laboratory systems, imaging, devices, sensors, electronic health records, and other digital sources. The Society for Clinical Data Management describes this evolution as a shift from an EDC-centered model toward a broader clinical data ecosystem. [2]
At the same time, study teams may need technology for monitoring, site management, trial master file activities, training, consent, randomization, medical coding, safety workflows, payments, and analytics.
The result is not simply more software. It is a greater need to connect clinical data with the workflows that create, review, manage, and act on it.
Consider a multi-country medical device study involving EDC, DICOM imaging, participant-reported outcomes, site monitoring, investigator training, and independent event review. Each process has a different purpose, but all contribute to the same clinical program.
When those activities can be managed within a connected technology environment, sponsors can design workflows around the study rather than around the boundaries between individual applications.
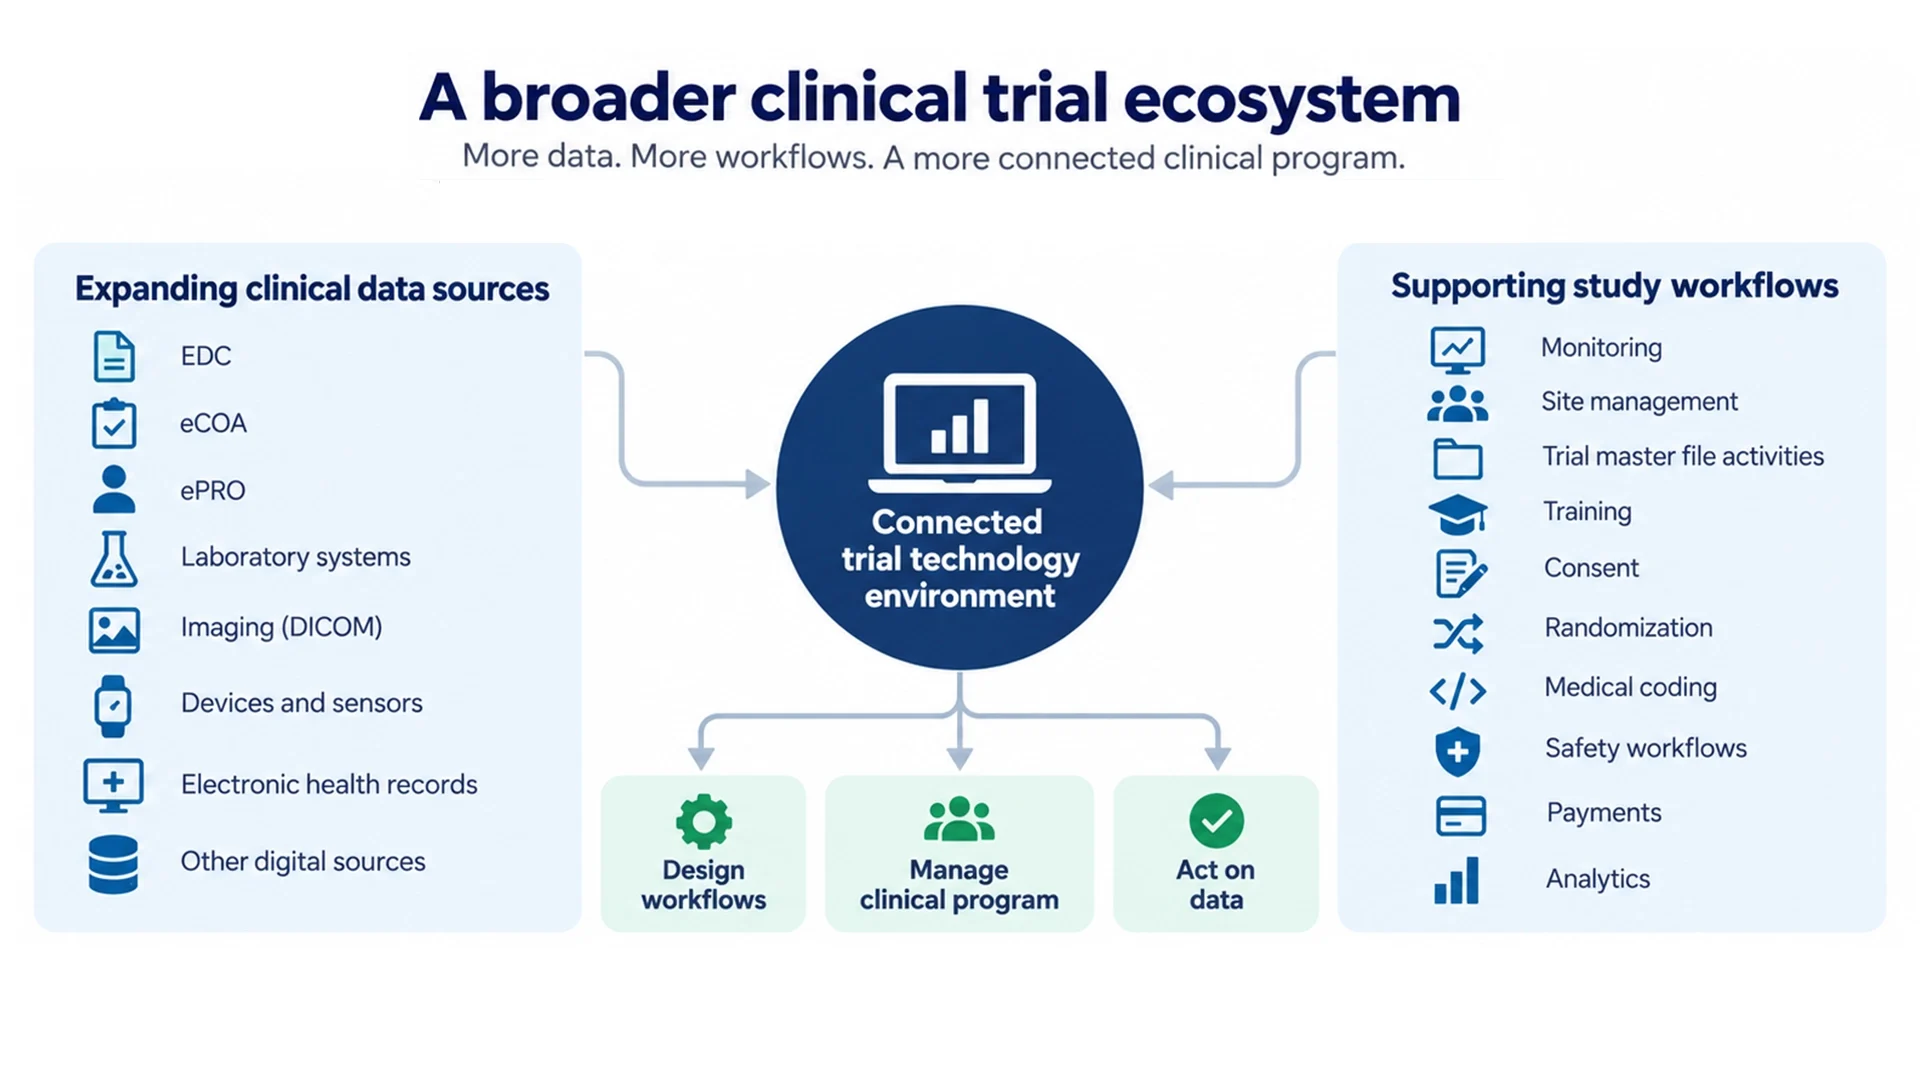
More trial data makes connected clinical trial software more valuable
The amount of information collected can become particularly significant in data-intensive therapeutic areas.
A 2025 peer-reviewed paper on scaling eSource in oncology clinical trials reported that modern Phase I oncology protocols can collect more than 27,000 data points per participant, over six times the average reported for non-oncology trials. It also noted that Phase III oncology studies can generate more than twice the volume of data collected in non-oncology Phase III trials. [3]
These figures are specific to oncology and should not be generalized to every clinical investigation. They illustrate, however, how quickly data requirements can expand when imaging, biomarkers, laboratory data, patient-reported information, and other sources enter the same protocol.
The practical implication is that data architecture and workflow architecture increasingly need to be considered together.
A clinical trial system needs to do more than store individual data points. Teams need appropriate access, traceability, review workflows, validation rules, operational visibility, and reliable connections between the different activities surrounding those data.
This is where an integrated eClinical model becomes particularly valuable.
Build the clinical research software stack around the study
A useful software architecture starts with the clinical workflow rather than a collection of isolated applications.
Different teams have different responsibilities. Data managers may focus on eCRF design, validation, queries, coding, and database readiness. Clinical operations teams need visibility into sites, milestones, enrollment, monitoring, and study progress. Participants and clinicians may interact with ePRO, eCOA, or eConsent applications. Investigators and site personnel also need study-specific training.
| Technology layer | Primary role in the study | Typical functions |
| Clinical data | Structure and manage trial data | EDC, eCRF, edit checks, medical coding |
| Trial operations | Coordinate study execution | CTMS, monitoring, milestones, site management |
| Participant interaction | Capture data and consent digitally | ePRO, eCOA, eConsent |
| Training | Prepare and document study teams | Protocol, system and procedural training |
| Intelligence | Support review and analysis | Analytics and AI-assisted workflows |
The architecture becomes especially powerful when these layers are designed to work together.
For example, participant-reported information collected electronically is more useful operationally when authorized study teams can access it within an appropriate clinical workflow. Similarly, training, monitoring, imaging, safety review, and site activities become easier to coordinate when technology supports a common study structure.
What a connected clinical trial system changes
As the number of workflows increases, the way clinical trial systems are structured becomes increasingly important.
A connected approach can help sponsors manage related processes within a more coherent environment rather than treating each activity as a separate technology project.
| Study requirement | Separate system approach | Connected platform approach |
| User access | Access managed across multiple environments | Access can be coordinated through a common environment |
| Clinical and operational data | Managed within separate workflows | Related workflows can be connected more directly |
| Study configuration | Changes assessed system by system | Dependencies can be considered across the study architecture |
| Participant data | May require separate applications and transfers | Participant-facing workflows can connect with the clinical data environment |
| Training | Managed independently from other study functions | Training can form part of the broader study technology model |
| Specialized workflows | Additional platforms may be required | Functions such as imaging, coding, and adjudication can be incorporated into the wider stack |
| Oversight | Information viewed across multiple interfaces | Centralized access can support broader study visibility |
For sponsors, this creates an opportunity to simplify the technology architecture without simplifying the study itself.
The protocol can remain sophisticated while the supporting digital environment becomes more coordinated.
How Medigen Suite brings the clinical trial software stack together
Medigen Suite is designed around this connected model.
The platform combines clinical data capture, centralized trial management, medical imaging, participant-facing applications, training, and AI-supported capabilities within one modular eClinical ecosystem. Its product family includes Catchtrial EDC+, Maptrial CTMS+, Catchtrial Apps+, Mastertrial LMS+, and Fastrial AI+.
Catchtrial EDC+ provides the clinical data foundation. Its broader platform capabilities include configurable electronic data capture together with specialized functionality such as DICOM imaging, randomization, safety adjudication, and MedDRA medical coding.
This is particularly relevant for studies where important clinical workflows extend beyond conventional eCRFs. Imaging and event-review activities, for example, can remain closer to the clinical data environment rather than becoming completely separate processes.
Maptrial CTMS+ extends the architecture into trial operations and oversight. It supports the management of studies, countries, sites, monitoring, milestones, documentation, and other operational activities within the broader Medigen Suite environment.
Catchtrial Apps+ connects participant and clinician-facing activities with the study. The suite includes ePRO, eCOA, and eConsent. Catchtrial ePRO integrates with the EDC so patient-reported information can flow into the clinical data environment, while eCOA supports configurable assessments, automated scoring, multilingual deployment, and centralized data access.
Mastertrial LMS+ adds the training layer. It can be used to deliver structured training for investigators, coordinators, monitors, and other study stakeholders across areas such as protocols, amendments, medical devices, EDC systems, ePRO tools, imaging workflows, and study procedures. Training completion records and dashboards support traceability across distributed study teams.
Fastrial AI+ provides the intelligence layer, extending AI-assisted capabilities across appropriate areas of the clinical technology environment.
Medigen Suite also offers a secure, centralized single sign-on web interface for access to study data and platform functions. Its modular design allows sponsors to select and configure capabilities around the needs of the clinical study rather than building an entirely separate technology environment for each workflow.
The result is a positive architectural principle: one connected ecosystem, configured around the study.
For sponsors reviewing their technology strategy, Medigen Suite provides an overview of how these capabilities can be combined.
Good clinical trial technology also supports strong governance
Connectivity needs to be accompanied by appropriate computerized system governance.
ICH E6(R3), finalized in January 2025, includes explicit expectations for computerized systems used in clinical trials. These cover areas such as procedures for system use, training, security, validation, user management, backup, contingency planning, and change control. The guideline also establishes a risk-based approach to validation based on the intended use of the system and the importance of the data or activities it supports. [4]
For FDA-regulated investigations, the FDA’s October 2024 final guidance on electronic systems, electronic records, and electronic signatures provides recommendations for maintaining electronic records that are trustworthy, reliable, and appropriate for regulatory use. [5]
For studies processing personal data under the General Data Protection Regulation (GDPR), the regulatory framework also establishes principles including purpose limitation, data minimization, accuracy, storage limitation, integrity and confidentiality, and accountability. [6]
For sponsors, these requirements reinforce the value of considering access controls, system configuration, traceability, validation, and data governance as part of the technology architecture from the beginning.
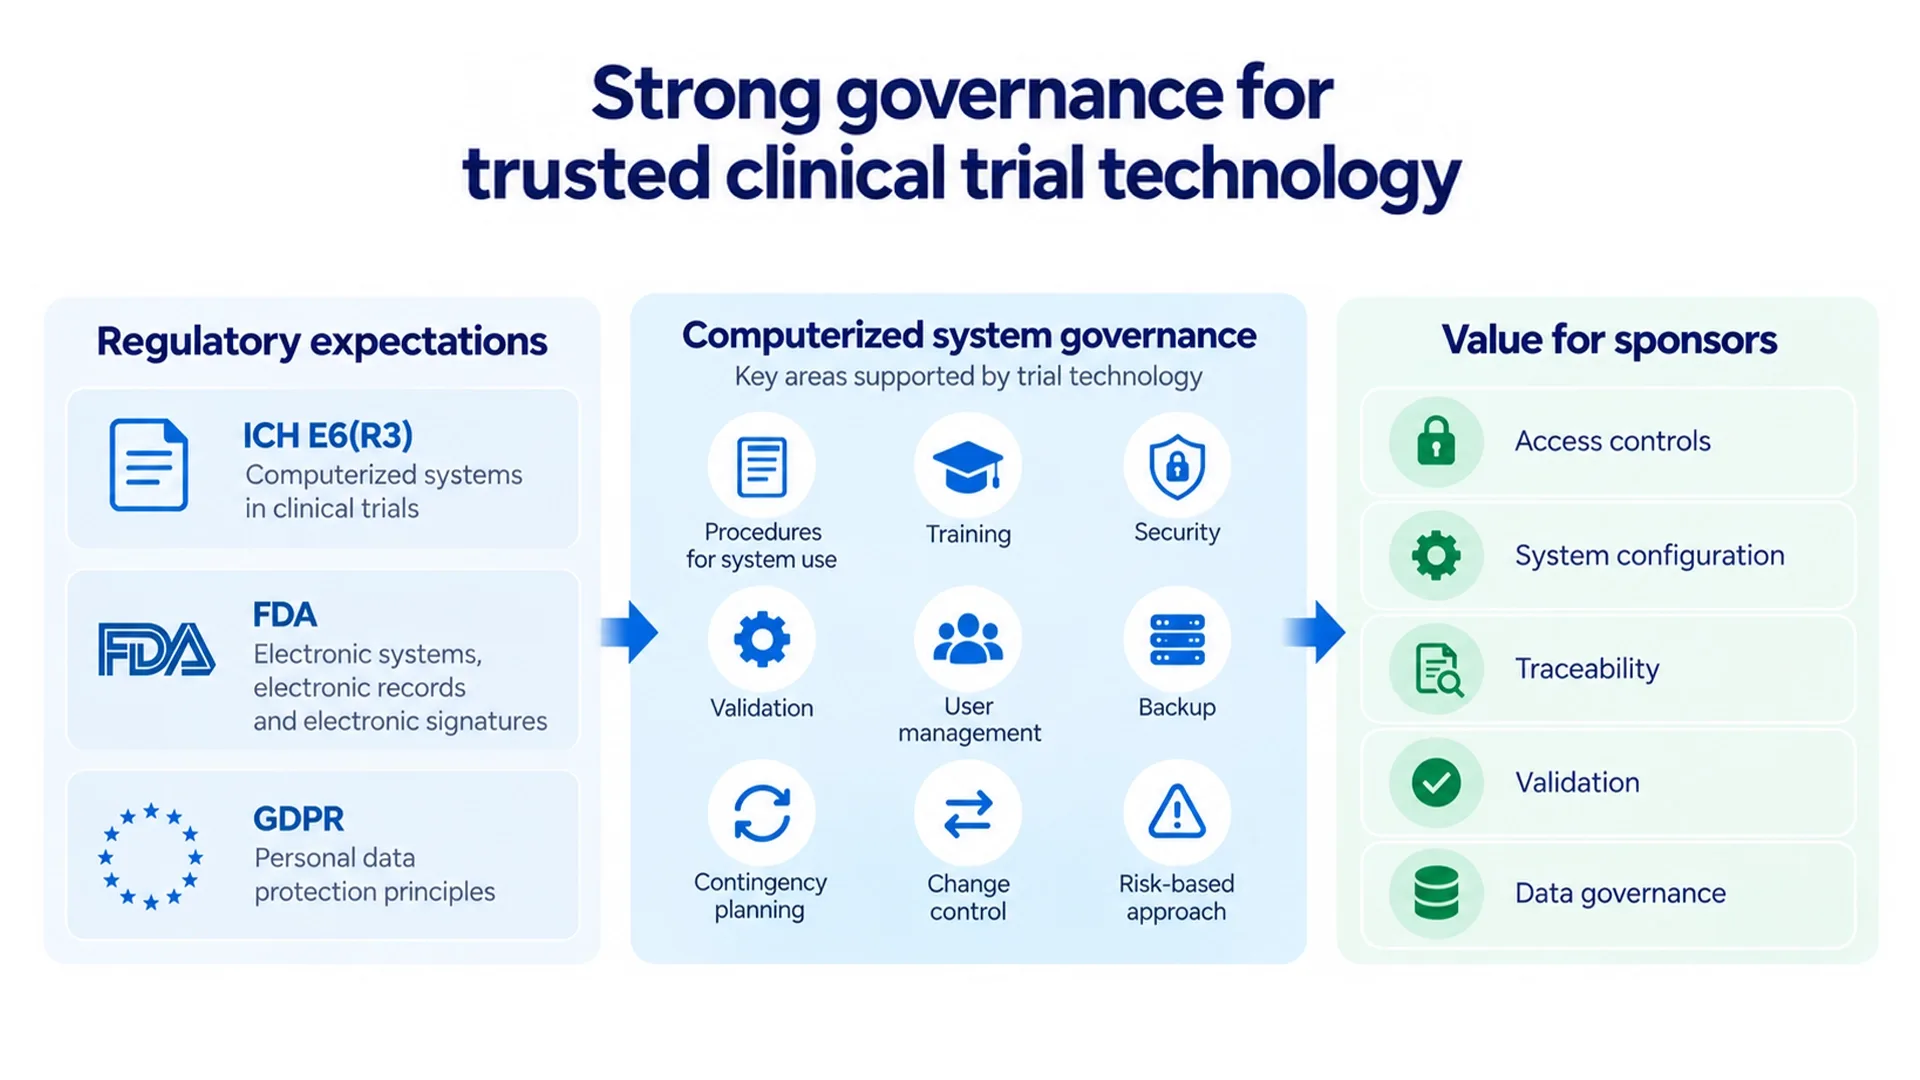
Choosing a clinical trial system for the study ahead
The technology decision should ultimately reflect the complexity of the protocol and the workflows required to execute it.
A sponsor planning a study involving EDC, imaging, ePRO, monitoring, training, and independent event review is not making six unrelated technology decisions. Those activities form part of one clinical operating model.
The most useful questions therefore focus on connectivity:
- Which clinical and operational workflows need to interact?
- Where will clinical, imaging, and participant-reported data be managed?
- How will study roles and access privileges be controlled?
- How will monitoring and operational oversight connect with the study?
- How will investigators and site teams receive and document training?
- Which specialized workflows, such as safety adjudication or medical coding, need to sit close to the EDC?
- How can AI and analytics be introduced within a controlled clinical environment?
The numbers behind modern trials make the direction clear. Millions of data points, hundreds of protocol procedures, and a growing variety of digital sources require technology capable of supporting more than isolated data capture.
Medigen Suite brings those requirements together in a modular eClinical environment designed around connected clinical research.
From EDC and DICOM imaging to CTMS, ePRO, eCOA, eConsent, training, safety adjudication, medical coding, and AI, the platform gives sponsors a broad technology foundation that can be configured around the needs of the study.
Visit the Medigen Suite website or request a demo to see how the platform can support your next clinical program.
Frequently Asked Questions
What should sponsors look for in clinical trial software?
Sponsors should look beyond individual features and consider the complete study architecture. Key areas include EDC, operational oversight, participant data collection, imaging, training, user access, validation, data governance, integrations, and specialized workflows. A connected platform can help bring these activities into a more coordinated technology environment.
Why is clinical research software becoming more important?
Clinical research software is becoming more important as trials generate larger and more diverse datasets. An analysis of completed Phase II and III protocols found an average of 263 procedures per participant, while Phase III trials generated approximately 3.6 million data points on average within the analyzed dataset. [1]
What does a modern clinical trial software stack include?
A modern stack may include EDC, CTMS, eTMF functionality, ePRO, eCOA, eConsent, imaging, randomization, safety adjudication, medical coding, training, analytics, and AI. Which capabilities are required depends on the clinical protocol and operating model.
Why connect clinical and operational systems?
Connecting clinical and operational systems can help teams work within a more coherent study environment. Clinical data, site activities, monitoring, participant workflows, training, imaging, and other processes are all parts of the same trial. A connected architecture is designed to make those relationships easier to manage.
What products are included in Medigen Suite?
Medigen Suite includes Catchtrial EDC+, Maptrial CTMS+, Catchtrial Apps+, Mastertrial LMS+, and Fastrial AI+. Together they cover clinical data capture, trial operations, ePRO, eCOA, eConsent, study training, and AI-supported workflows, with additional capabilities including medical imaging, randomization, safety adjudication, and medical coding.
How does Medigen Suite support a connected technology strategy?
Medigen Suite brings complementary clinical trial functions into one modular ecosystem and provides centralized access through a secure single sign-on web interface. Sponsors can configure the platform around study requirements while keeping clinical data, operations, participant workflows, training, and specialized functions within a connected technology model.
Sources
- Tufts Center for the Study of Drug Development. Rising Protocol Design Complexity Is Driving Rapid Growth in Clinical Trial Data Volume. January 2021.
- Society for Clinical Data Management. The Evolution of Clinical Data Management into Clinical Data Science: A Reflection Paper on the Impact of Clinical Research Industry Trends on Clinical Data Management. June 2019.
- European Institute for Innovation through Health Data and collaborators. Accelerating eSource scale-up in oncology clinical trials: The i~HD Task Force initiative. 2025.
- International Council for Harmonisation. ICH Harmonised Guideline E6(R3): Guideline for Good Clinical Practice. Final version, January 6, 2025.
- S. Food and Drug Administration. Electronic Systems, Electronic Records, and Electronic Signatures in Clinical Investigations: Questions and Answers. Final Guidance, October 2024.
- European Commission. Principles of personal data processing under the GDPR
Table of Contents
Latest Articles

21 CFR Part 11 password requirements: what the regulation actually says
A 90-day password change is not a 21 CFR [...]
Clinical trial software for the connected study stack
Clinical trials are generating more data from more sources, [...]

A practical guide to the main types of clinical trials
The type of clinical trial you run shapes almost [...]
This article provides general information and does not constitute regulatory, legal, clinical, or compliance advice. Requirements and appropriate processes may vary by study, product, jurisdiction, and organization. Medigen Suite functionality should be used in accordance with applicable regulations, study documentation, and internal procedures.
